Introduction
A renal biopsy report can provide valuable information about the nature and extent of kidney disease. However, understanding the report requires more than recognising individual medical terms. The findings must be interpreted alongside clinical symptoms, laboratory investigations, imaging results and the patient's medical history.
Renal biopsy examination can reveal abnormalities involving the glomeruli, tubules, interstitium and blood vessels. It can also help distinguish active inflammation from chronic structural damage in selected cases.
For medical professionals interested in developing a deeper understanding of kidney tissue interpretation, the Fellowship in Renal Pathology is a relevant educational option to explore. Understanding the terminology and structure of renal biopsy reports can provide a useful foundation for studying complex kidney disorders.
1. Why Is a Renal Biopsy Performed?
A renal biopsy involves collecting a small sample of kidney tissue for microscopic examination. It is considered when the expected diagnostic benefit justifies the procedure and the findings may influence clinical decisions.
A biopsy may be considered in selected patients with unexplained kidney dysfunction, significant proteinuria, suspected glomerular disease or certain systemic conditions affecting the kidneys.
However, not every patient with abnormal kidney function requires a biopsy. The decision depends on the clinical presentation, alternative investigations, potential risks and whether the results are likely to provide meaningful information.
Once tissue is obtained, the sample is assessed using appropriate laboratory techniques. The final report brings together the observed structural changes and other relevant diagnostic findings.
2. Understanding the Main Sections of a Renal Biopsy Report
Although report formats vary between laboratories, several components commonly contribute to renal biopsy interpretation.
Clinical information
The clinical information section summarises the reason for the biopsy and relevant patient findings. These may include kidney function measurements, proteinuria, haematuria, blood pressure, suspected systemic disease and other relevant investigations.
This information helps place the microscopic findings into context.
Light microscopy findings
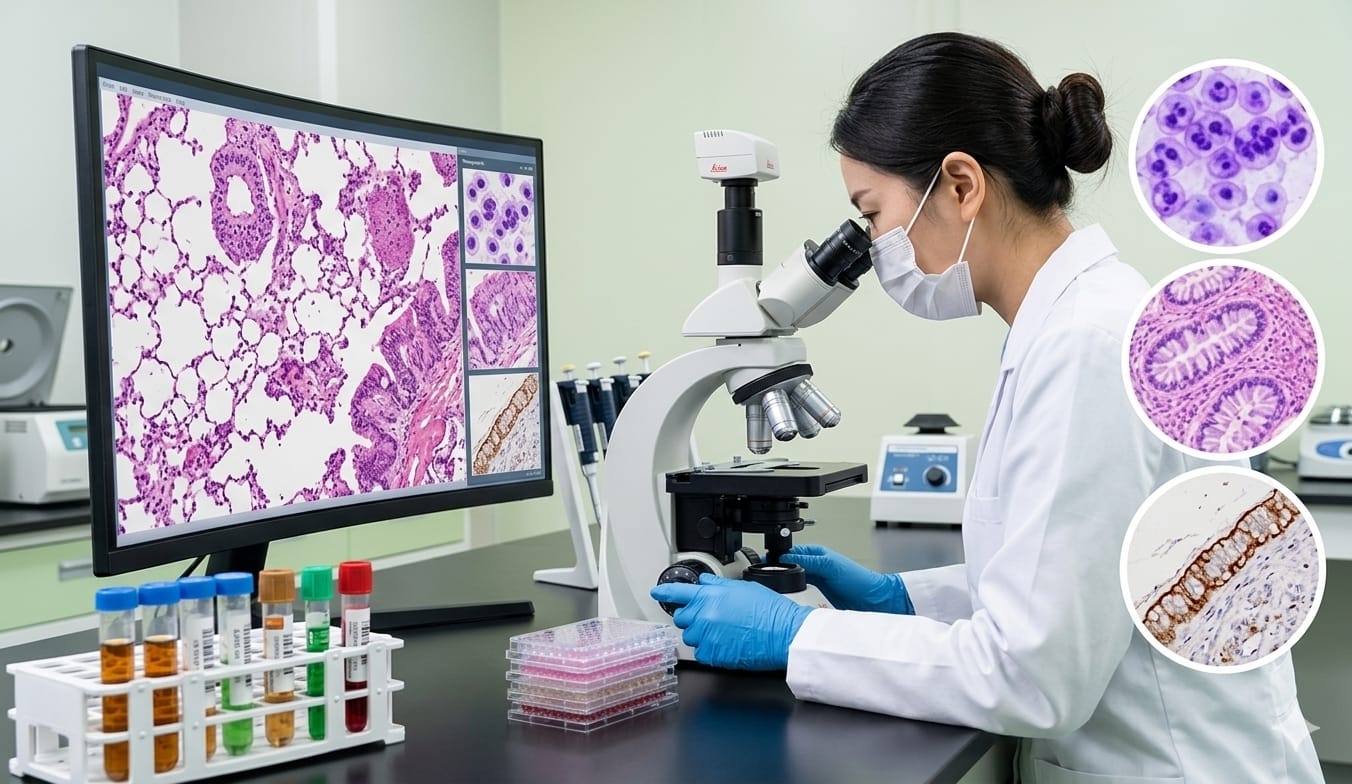
Light microscopy allows the pathologist to examine kidney tissue architecture and identify structural abnormalities.
The report may describe glomerular changes, tubular injury, interstitial inflammation, fibrosis or vascular abnormalities. It may also document how many glomeruli are present and whether the observed changes are focal or more widespread.
Immunofluorescence findings
Immunofluorescence can help identify the distribution of immunoglobulins and complement components within kidney tissue.
The pattern of staining may support the investigation of immune-mediated kidney diseases. However, immunofluorescence findings must be interpreted alongside clinical information and other biopsy results.
Electron microscopy findings
Electron microscopy provides detailed information about tissue ultrastructure. Depending on the suspected condition, it may help identify changes in the glomerular basement membrane, podocyte foot processes or electron-dense deposits.
Not every biopsy requires every technique. The choice depends on the diagnostic question, specimen availability and laboratory practice.
3. What Do Glomerular Findings Mean?
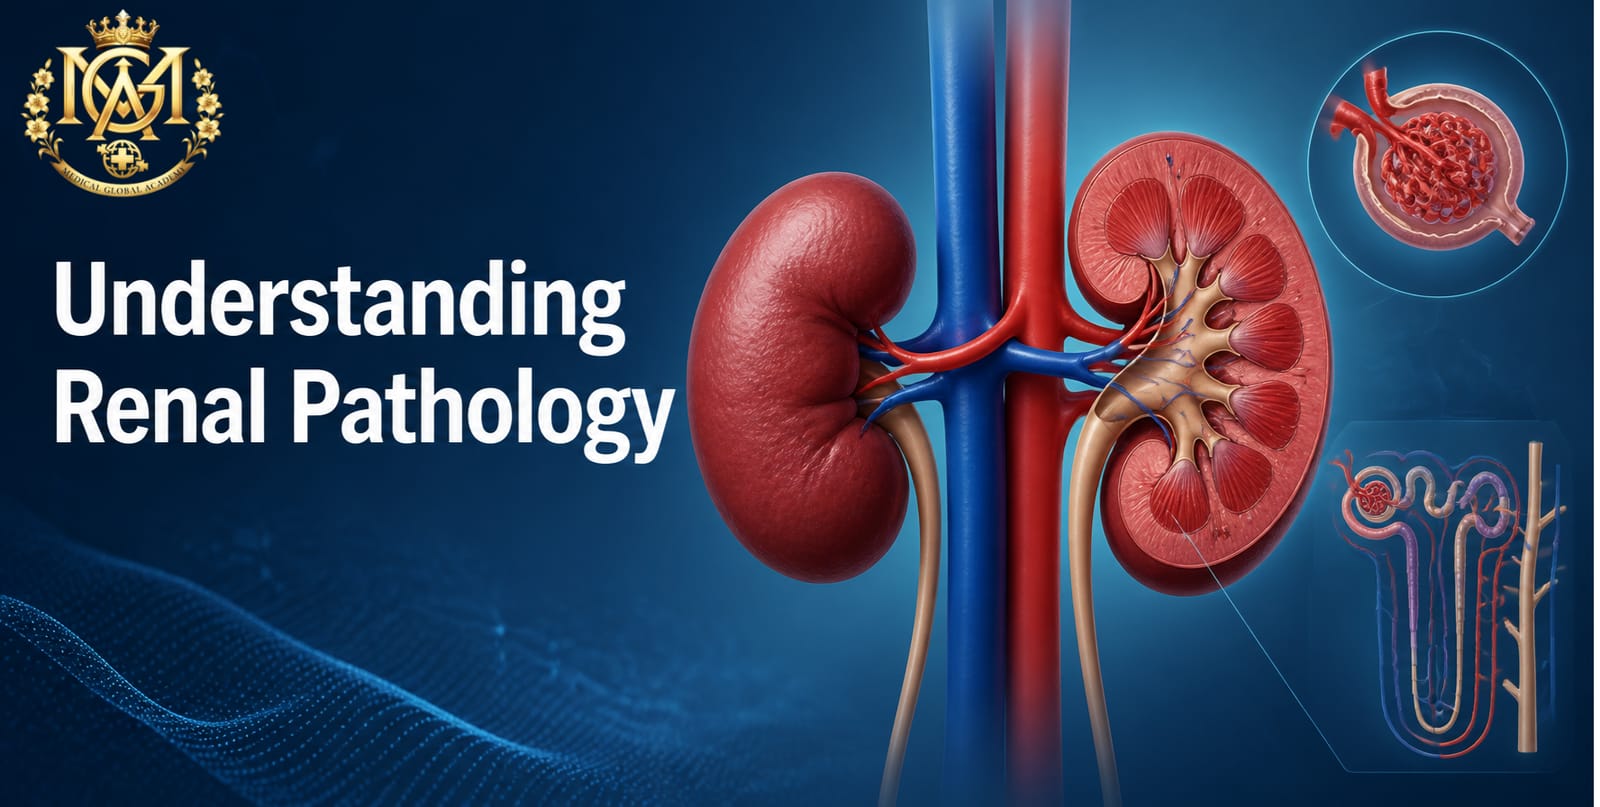
The glomeruli are specialised structures responsible for filtering blood. Abnormalities in these structures may be associated with proteinuria, haematuria and declining kidney function.
A renal biopsy report may describe several types of glomerular changes.
Proliferation: An increase in the number of cells within particular glomerular compartments may occur in inflammatory or immune-mediated disorders.
Sclerosis: This term describes scarring within tissue. Glomerular sclerosis may reflect chronic damage, although its significance depends on the overall pattern and clinical context.
Crescent formation: Crescents are cellular or fibrocellular structures that may develop in Bowman's space in association with severe glomerular injury.
Capillary wall abnormalities: Changes affecting glomerular capillary walls or the basement membrane may provide important diagnostic clues in selected disorders.
These terms describe tissue appearances rather than complete diagnoses. Their significance depends on the distribution, severity and combination of findings.
4. Understanding Tubular and Interstitial Changes
Renal biopsy interpretation is not limited to glomeruli. Tubules and the surrounding interstitial tissue can also provide important evidence about the underlying disease.
Tubular injury
Tubular injury may occur during acute kidney injury, ischaemia, exposure to certain nephrotoxic substances or other conditions affecting renal tubular cells.
A report may describe epithelial damage, loss of normal cellular architecture or material within tubular lumens. These findings should be interpreted alongside the patient's clinical history and laboratory results.
Interstitial inflammation
Inflammatory cells within the renal interstitium may be associated with several conditions, including certain drug reactions and inflammatory disorders.
The type and distribution of inflammatory cells, along with other tissue findings, can help refine the differential diagnosis.
Interstitial fibrosis and tubular atrophy
Interstitial fibrosis describes the accumulation of scar-like connective tissue, while tubular atrophy refers to a reduction in normal tubular structure.
These findings can indicate chronic kidney damage. Their extent may provide useful prognostic information, but they cannot independently determine an individual patient's outcome.
5. Why Immunofluorescence and Electron Microscopy Matter
Some kidney diseases have overlapping clinical presentations but different tissue characteristics. Additional microscopy techniques may help distinguish between these conditions.
Immunofluorescence evaluates the location and pattern of selected immune-related substances in the tissue. For example, the distribution of immunoglobulins and complement may support the investigation of particular immune-mediated glomerular disorders.
Electron microscopy offers greater detail about the ultrastructure of kidney tissue. It may reveal abnormalities that are difficult to assess using routine light microscopy alone.
The combined interpretation of these techniques can strengthen diagnostic assessment when used appropriately. Nevertheless, neither technique should be interpreted in isolation, and the absence or presence of a particular finding must be considered in the context of the complete case.
6. Active Disease Versus Chronic Damage
One important task in renal biopsy interpretation is distinguishing active injury from established structural damage.
Active inflammatory changes may indicate an ongoing disease process. In contrast, sclerosis, interstitial fibrosis and tubular atrophy often reflect chronic injury.
Some biopsies demonstrate both active and chronic changes. For example, a patient with longstanding kidney disease may develop a new inflammatory process that contributes to a recent decline in kidney function.
Recognising these components can help explain why a patient's current clinical condition differs from their previous baseline.
However, pathology findings do not independently determine treatment. Clinical decisions require integration of the biopsy report with symptoms, laboratory measurements, disease history and other relevant evidence.
7. Common Challenges When Reading Renal Biopsy Reports
Medical terminology can make renal biopsy reports difficult to interpret, particularly when several abnormalities appear together.
One common challenge is assuming that a single finding establishes a specific diagnosis. In reality, many tissue features occur in more than one disease.
Another challenge is overlooking the distribution of abnormalities. A focal lesion affecting a limited number of glomeruli may have a different interpretation from a similar lesion distributed widely throughout the sample.
Sampling limitations also matter. A biopsy represents a small portion of the kidney, so the findings must be interpreted with awareness that not every area of tissue is represented.
Finally, the clinical context should never be ignored. The same microscopic finding may have different implications depending on the patient's age, medical history, laboratory results and suspected condition.
These considerations explain why renal biopsy interpretation requires a structured approach and appropriate specialist expertise.
8. Developing Knowledge of Renal Pathology
A strong foundation in renal pathology involves understanding kidney anatomy, mechanisms of injury, microscopy techniques and the terminology used in diagnostic reports.
Doctors exploring further academic learning may consider the Fellowship in Renal Pathology when comparing educational programmes. Before enrolling, prospective learners should review the curriculum, eligibility requirements, teaching methods and stated learning outcomes.
Structured study can help learners build conceptual familiarity with renal disorders and the interpretation of tissue findings. The relevance of any programme depends on its content and the learner's professional objectives.
Educational programmes should not be confused with supervised clinical training or specialist accreditation unless those features are explicitly included and appropriately recognised.
Conclusion
Renal biopsy reports provide important information about the structural changes associated with kidney disease. Understanding their findings requires familiarity with glomerular abnormalities, tubular injury, interstitial changes, fibrosis and the complementary roles of light microscopy, immunofluorescence and electron microscopy.
The most meaningful interpretation comes from combining these observations with clinical history, laboratory results and other diagnostic evidence. Individual findings should not be treated as definitive diagnoses without appropriate context.
For medical professionals interested in developing a stronger academic understanding of these concepts, the Fellowship in Renal Pathology is an option to investigate when reviewing relevant educational opportunities.
A systematic approach to renal biopsy interpretation can make complex pathology terminology easier to understand and clarify how tissue findings contribute to the broader evaluation of kidney disease.